
[Sep 10, 2026] Latest CPHQ Exam with Accurate Certified Professional in Healthcare Quality Examination PDF Questions
Practice To CPHQ - UpdateDumps Remarkable Practice On your Certified Professional in Healthcare Quality Examination Exam
NEW QUESTION # 183
A performance improvement specialist at an ambulatory surgery center is facilitating a Plan-Do- Study-Act Cycle (PDSA) process to improve the rate of hand hygiene amongst surgical post-recovery staff to 90% or above.
Data from the past 12 months are as follows:
Baseline: 60% compliance
Q1: 87% compliance
Q2: 79% compliance
Q3: 91% compliance
Q4: 72% compliance
The specialist is preparing to discuss aggregate results with the Quality Committee. To most accurately convey the results, the specialist highlights the
- A. sharp and consistent decline in results over the past 12 months.
- B. contributing factors to the variation in results over the past 12 months.
- C. lack of overall change over the past 12 months indicates the process was unsuccessful.
- D. overall improvement over the past 12 months.
Answer: B
Explanation:
When discussing the aggregate results of the PDSA cycle to improve hand hygiene compliance, it is crucial to highlight the contributing factors to the variation in results over the past 12 months. The data shows fluctuations in compliance rates, with a peak in Q3 and declines in Q2 and Q4. Analyzing and understanding the reasons behind these variations is essential for identifying what worked well and what challenges arose. This approach allows the Quality Committee to develop strategies to address the inconsistencies and sustain improvements.
Lack of overall change (A): This statement is inaccurate as there were periods of significant improvement, especially in Q1 and Q3.
Sharp and consistent decline (C): This is misleading, as the data does not show a consistent decline; rather, it shows fluctuations.
Overall improvement (D): While there was some improvement, the focus should be on understanding the causes of the variability rather than just the overall trend. Reference NAHQ Body of Knowledge: Performance and Process Improvement NAHQ CPHQ Exam Preparation Materials: PDSA Cycle and Data Analysis
NEW QUESTION # 184
The following hospital Medicare readmission findings are available: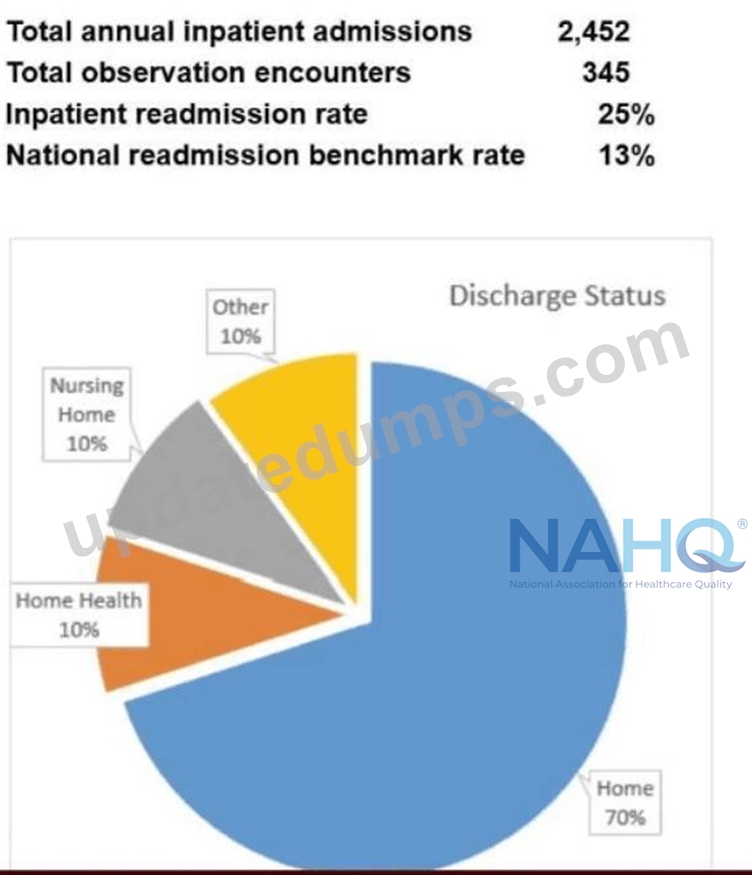
Based on the provided information and an understanding of factors that drive readmissions, the hospital should first
- A. instruct physicians to place patients in observation whenever possible.
- B. work with the medical staff to increase follow-up visits after discharge.
- C. initiate post-discharge follow-up calls.
- D. analyze data to determine the best approach for readmission reduction.
Answer: D
Explanation:
Reducing Medicare readmissions is a key focus in population health, as readmissions impact patient outcomes and hospital reimbursement under programs like the Hospital Readmissions Reduction Program (HRRP).
Factors driving readmissions often include inadequate discharge planning, lack of follow-up care, social determinants of health (e.g., transportation, support systems), and patient-specific risks (e.g., comorbidities).
NAHQ CPHQ study materials emphasize a systematic, data-driven approach to quality improvement, particularly for complex issues like readmissions.
Since the specific Medicare readmission findings are not provided, I'll base the answer on CPHQ best practices. The first step in addressing readmissions should always be to analyze data to determine the best approach for readmission reduction (D). This involves reviewing the readmission findings to identify patterns, such as high-risk patient groups, common diagnoses (e.g., heart failure, pneumonia), or process failures (e.g., medication reconciliation issues). Data analysis helps pinpoint root causes and informs targeted interventions, ensuring resources are used effectively. For example, if data show readmissions are due to lack of follow-up care, then strategies like follow-up calls or visits can be prioritized. Without this analysis, interventions may be misdirected.
Instructing physicians to place patients in observation (A) may reduce reported readmissions by reclassifying stays, but this does not address underlying causes and could be seen as gaming the system, which is not aligned with quality improvement principles. Initiating post-discharge follow-up calls (B) or increasing follow-up visits (C) are potential interventions, but they assume specific causes (e.g., lack of follow-up) without evidence from the data. NAHQ emphasizes that quality improvement starts with understanding the problem through data analysis, making option D the first step.
Reference: NAHQ CPHQ Study Guide, Population Health and Care Transitions Section, "Readmission Reduction Strategies"; NAHQ CPHQ Practice Exam, Data-Driven Quality Improvement for Population Health.
NEW QUESTION # 185
A patient was in the operating room when a piece of a surgical instrument broke off and was left in the patient's body. The patient was readmitted for removal of the foreign object.
Which of the following would most likely apply in this situation?
- A. Contributory negligence
- B. Tort liability
- C. Contractual liability
- D. Res ipsa loquitur
Answer: D
NEW QUESTION # 186
An organization has compiled the scatter plots below: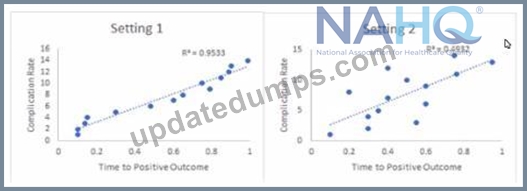
Based on these plots, which of the following conclusions can be made by the quality professional?
- A. Setting 2 has a significant correlation between complication rate and time to positive outcome.
- B. Complication rates are causing longer time to positive outcome at settling 1.
- C. Complication rates are not causing longer time to positive outcome at setting 2.
- D. Setting 1 has a strong positive correlation between complication rate and time to positive outcome.
Answer: D
Explanation:
* A scatter plot is a graphical tool that shows the relationship between two continuous variables by plotting data points at their corresponding values on the x-axis and y-axis1.
* To interpret a scatter plot, we need to look at the direction, strength, and shape of the relationship between the variables2.
* The direction of the relationship indicates whether the variables tend to increase or decrease together (positive correlation) or in opposite directions (negative correlation).
* The strength of the relationship indicates how closely the data points cluster around a line or curve that best fits the data. A common measure of the strength of the linear relationship is the correlation coefficient , which ranges from -1 to 1. The closer the absolute value of R is to 1, the stronger the linear relationship2.
* The shape of the relationship indicates whether the data points follow a straight line (linear relationship) or a curved pattern (nonlinear relationship).
* Based on these criteria, we can analyze the scatter plots for Setting 1 and Setting 2 as follows:
* Setting 1: The scatter plot shows a clear upward trend, indicating a positive correlation between complication rate and time to positive outcome. The data points are tightly clustered around a line, indicating a strong linear relationship. The R^2 value of 0.9533 on the plot is close to 1, which means that the linear model explains 95.33% of the variation in the complication rate.
Therefore, we can conclude that Setting 1 has a strong positive correlation between complication rate and time to positive outcome.
* Setting 2: The scatter plot shows a scattered pattern, indicating a weak or no correlation between complication rate and time to positive outcome. The data points are widely spread around a line, indicating a weak linear relationship. The R^2 value of 0.4923 on the plot is far from 1, which means that the linear model explains only 49.23% of the variation in the complication rate.
Therefore, we cannot conclude that Setting 2 has a significant correlation between complication rate and time to positive outcome, or that complication rates are causing longer time to positive outcome at setting 2.
References: 1: 8.8 Scatter Plots, Correlation, and Regression Lines 2: Scatterplots: Using, Examples, and Interpreting
NEW QUESTION # 187
A researcher decides to look at every fourth patient admitted each day and record if the IV is properly labeled, starting with a randomly selected patient. This is known as which of the following types of random selection?
- A. Convenience
- B. Systematic
- C. Simple
- D. Stratified
Answer: B
Explanation:
Detailed Explanation:
Systematic sampling involves selecting every nth individual from a list or sequence after a random start.
Option C: Systematic
By choosing every fourth patient after a random start, the researcher is using systematic sampling.
Option A: Simple
Simple random sampling would involve selecting individuals at random, without a set interval.
Options B and D:
Convenience sampling is based on ease of access, and stratified sampling divides the population into subgroups before random selection.
References:
Systematic sampling is well-described in research methods literature, where interval selection following a random start is a key feature.
NEW QUESTION # 188
Many organizations establish condition-specific patient registries for their more sophisticated quality improvement projects because they do not have a reliable source of clinical information.
The use of patient registries is advantageous for the following reasons EXCEPT:
- A. They are rich source of information because they are customized
- B. They can be used for quality improvements and research purposes
- C. They are not subject to short comings of review records
- D. They can collect all the data that the physician or health system determines are most important
Answer: C
NEW QUESTION # 189
The chart shown below is created for a project schedule.
What is the minimum number of days required to complete the project?
- A. 0
- B. 1
- C. 2
- D. 3
Answer: B
Explanation:
According to the NAHQ CPHQ exam blueprint, project scheduling tools such as network diagrams and critical path analysis are core competencies within Performance and Process Improvement. The critical path represents the longest sequence of dependent tasks and determines the minimum time required to complete a project.
In this project diagram, tasks occur in parallel paths with defined durations. To determine the minimum project duration, all possible paths must be evaluated, and the longest cumulative duration must be identified.
When the task dependencies and durations are correctly followed, the critical path totals 25 days, which establishes the shortest possible completion time for the project.
Shorter paths (such as those totaling 15 days) do not control project completion because they finish earlier and contain slack time. Options C and D represent inflated timelines that do not align with the calculated critical path.
The CPHQ framework emphasizes accurate interpretation of project management tools to support realistic planning, resource allocation, and performance improvement initiatives. Correct identification of the critical path ensures timelines are achievable and risks are appropriately managed.
NEW QUESTION # 190
The strategic plan for an organization calls for expansion of information technology. The following information is available: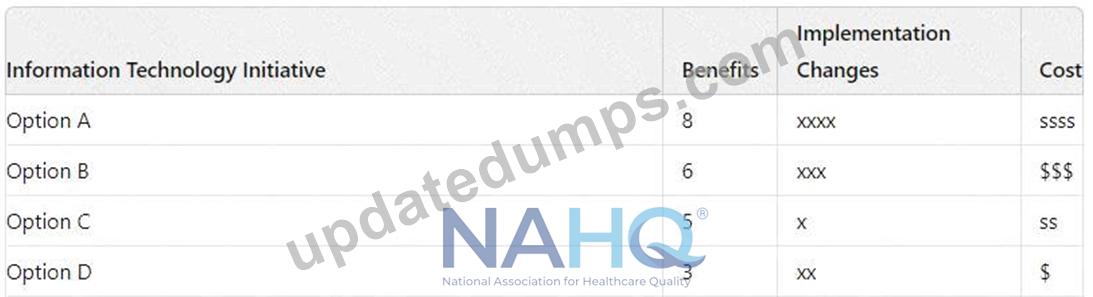
If equal weight is given to each consideration, which of the following options should be the primary choice?
- A. Option C
- B. Option B
- C. Option A
- D. Option D
Answer: A
Explanation:
If equal weight is given to each consideration (Benefits, Implementation Changes, and Cost), Option C should be the primary choice. The rationale is as follows:
* Benefits: While Option A has the highest benefit score (8), Option C's benefit score of 5 is still relatively strong.
* Implementation Changes: Option C has the fewest implementation changes ("x"), suggesting it will be easier to implement.
* Cost: Option C is the second most cost-effective option ("$$"), balancing cost against benefits and implementation changes.
Option C strikes a balance between benefits, ease of implementation, and cost, making it a solid choice when all factors are weighted equally.
* Option A (A): Although it offers the highest benefits, it also has the highest cost ("$$$$") and the most implementation changes ("xxxx").
* Option B (B): This option has slightly lower benefits, moderate implementation changes, and high cost ("$$$").
* Option D (D): Although it has the lowest cost, the benefits are also the lowest, making it less attractive overall.
References
* NAHQ Body of Knowledge: Strategic Decision-Making in IT Initiatives
* NAHQ CPHQ Exam Preparation Materials: Cost-Benefit Analysis in Healthcare Projects
NEW QUESTION # 191
Which of the following is an important characteristic of a performance indicator?
- A. measurable
- B. outcome-oriented
- C. process-oriented
- D. time-limited
Answer: A
Explanation:
Explanation: Performance indicators must be measurable (C) to allow objective data collection and analysis.
Time-limited (A), process-oriented (B), and outcome-oriented (D) are not universal requirements. NAHQ prioritizes measurability as a core characteristic.
NAHQ CPHQ Study Guide, Performance and Process Improvement Section, "Performance Indicators and Metrics"; NAHQ CPHQ Practice Questions, Quality Measurement.
NEW QUESTION # 192
A patient safety manager provided training on hand hygiene guidelines. The clinical manager Is confident that staff are following the guidelines.
Which of the following Is the best method to evaluate the current compliance with the guidelines?
- A. a test with a passing score of 98%
- B. collection of bacterial hand cultures
- C. direct observation of staff
- D. calculation of Infection rates compared to a baseline
Answer: C
Explanation:
According to the WHO Guidelines on Hand Hygiene in Health Care, direct observation of hand hygiene practices is the gold standard for measuring compliance1. Direct observation allows for the assessment of the five moments of hand hygiene, the use of appropriate technique, and the identification of barriers and facilitators to adherence1.
Direct observation also provides an opportunity for immediate feedback and education to the health care workers, which can improve their knowledge and motivation to perform hand hygiene2. Direct observation can be done covertly or overtly, depending on the purpose and context of the audit2.
Other methods of measuring hand hygiene compliance, such as collection of bacterial hand cultures, calculation of infection rates, or a test with a passing score, have limitations and disadvantages. For example, bacterial hand cultures may not reflect the actual transmission of pathogens, infection rates may be influenced by many factors other than hand hygiene, and a test score may not correlate with actual behavior2.
Reference: 1: WHO Guidelines on Hand Hygiene in Health Care, WHO, 2009 2: Hand Hygiene:
Education, Monitoring and Feedback, CDC, 2019
NEW QUESTION # 193
In an improvement project to improve clinic flow, a spaghetti chart is best used to:
- A. Analyze the suppliers, inputs, processes, outputs, and customers.
- B. Display the hierarchy of subtasks required to achieve an objective.
- C. Determine the strengths, weaknesses, opportunities, and threats of a process.
- D. Identify redundancies and wasted movement.
Answer: D
Explanation:
Detailed Explanation:
A spaghetti chart visually represents the physical path taken by staff or patients, helping identify inefficiencies, redundancies, and wasted movement.
Option B: Identify redundancies and wasted movement
Spaghetti charts highlight inefficiencies by mapping out excessive or unnecessary movement in the workflow.
References:
CPHQ resources on process improvement tools emphasize spaghetti charts for identifying movement inefficiencies.
NEW QUESTION # 194
The increased focus on and mandate for healthcare data place healthcare providers in a different situation than they have known in the past. Providers document such things and, unfortunately, many providers struggle to address the measurement mandate proactively, which leads organizations to assume a defensive posture when external organizations release the data.
Which of the following ways show/s the responses of provider in such cases? (Choose three.)
- A. The data are not stratified and do not represent appropriate comparisons.
- B. We can move in a better way without doing competition with others
- C. The data are old (typically one or two years) and do not reflect our current performance
- D. Our patients are siertan those at the other hospitals in our comparison group (i.e., no risk adjustments were made to the data).
Answer: A,C,D
NEW QUESTION # 195
A quality professional needs to select a new project from a list of requests. An organization has determined that new projects should focus on patient safety and cost-reduction.
Which tool would help Identify the project that best meets these criteria?
- A. lotus diagram
- B. value-stream map
- C. process decision program chart
- D. prioritization matrix
Answer: D
Explanation:
A prioritization matrix is a tool used in decision-making to compare and rank options based on specific criteria. It helps in identifying the most important or highest priority items from a list of options12. In the context of healthcare quality, when a professional needs to select a new project from a list of requests, and the organization has determined that new projects should focus on patient safety and cost-reduction, a prioritization matrix would be the most suitable tool. It would allow the professional to rank the projects based on these two criteria (patient safety and cost-reduction) and select the one that best meets these criteria12.
NEW QUESTION # 196
An organization Is tracking Infection rates to determine the benchmarks for the next fiscal year. The team Is analyzing the data for Infection rates. Which key variables are missing to interpret the graph?
- A. the quality of patients and hospital compliance with handwashing
- B. the timeframe for each data point andthe source (or the target line
- C. the mode of the data points and expected rate for external hospitals
- D. the standardized infection ratio for the previous year and denominator for each measure
Answer: B
Explanation:
The question pertains to key variables missing in a graph that tracks infection rates for benchmarking purposes. The options provided suggest various combinations of data that could potentially be missing, impacting the interpretation of the graph.
Option A suggests a need for historical data and specific denominators, but it doesn't address immediate contextual needs like timeframe or source/target lines.
Option C introduces external hospital expected rates and modes of data points, which might not be directly relevant to interpreting a specific organization's infection rate trends.
Option D focuses on qualitative aspects like patient quality and compliance with handwashing protocols, which are essential but not directly related to interpreting graphical data.
Option B is verified as correct because it highlights two critical elements: "the timeframe for each data point" and "the source (or target line)." These elements are fundamental to understanding any graph as they provide context regarding when the data was collected and what benchmarks or standards are being compared against.
The timeframe is essential to identify trends over time, seasonal variations, or impacts of specific interventions or changes in practice.
The source or target line provides a benchmark indicating expected performance levels or goals that the organization aims to achieve.
Without these two pieces of information, it would be challenging to derive meaningful insights from the graph about infection rate trends and their implications for future benchmarks.
References:
HQ Solutions: Resource for the Healthcare Quality Professional, Fifth Edition, Chapter 5: Quality Review and Accountability, p. 133-134 Learning Lab: Survey Readiness - A Team Approach to Success, Slide 8: Data Display Learning Lab: The Role of the Healthcare Quality Professional in Population Health Management, Slide 10:
Data Visualization
NEW QUESTION # 197
An optimal response rate is necessary to have a representative sample; therefore boosting response rates should be a
priority. Methods to improve response rates include all of the following EXCEPT:
- A. Offering incentives appropriate for the focus group population
- B. Making telephone reminder calls for certain types of surveys
- C. Ensuring that telephone numbers or addresses are drawn from as accurate rate a source as possible
- D. Using the Dillman method, a three wave mailing protocol designed to boost response rates
Answer: A
NEW QUESTION # 198
Measurement of variation in health care and its application to quality improvement must begin with the identification
and articulation of:
- A. Understanding true variation versus artifact or statistical error
- B. Assignable variation
- C. The standard against which is to be compared a process based on extensive research,
trial and error and collaborative discussion - D. What is to be measured?
Answer: B,C
NEW QUESTION # 199
The quality professional has been asked to perform chart audits on a population to assess how often hypertension is being addressed by clinicians when hypertensive patients presented to the clinic in the last year. The clinic has over 8,000 patients diagnosed with hypertension. Which of the following would be most appropriate for the quality professional to consider when selecting a sampling methodology?
- A. Selection of patients who had a visit during the last month of the year
- B. Selection of 800 patients using a snowball sampling method
- C. Selection of 400 charts using a simple random sampling method
- D. Selection of the entire population as a sample to make sure the results are accurate
Answer: C
Explanation:
Detailed Explanation:
For a large population, a simple random sample of 400 charts would be sufficient to obtain representative data for statistical analysis:
Option B: Selection of 400 charts using a simple random sampling method Simple random sampling ensures each patient has an equal chance of selection, providing unbiased and representative results while being more manageable than reviewing all 8,000 records.
Option A: Selection of patients who had a visit during the last month of the year This could lead to biased results, as it would not be representative of visits throughout the year.
Option C: Selection of 800 patients using a snowball sampling method
Snowball sampling is typically used for hard-to-reach populations and is not appropriate for this scenario.
Option D: Selection of the entire population
Auditing all records would be time-consuming and unnecessary when a statistically valid sample can provide reliable results.
References:
CPHQ guidelines and quality improvement literature support the use of simple random sampling for representative data collection in large populations.
NEW QUESTION # 200
Which of the following is a social determinant of health?
- A. High body mass index
- B. Poorly managed chronic condition
- C. Low literacy level
- D. Advanced age
Answer: C
Explanation:
Social determinants of health (SDOH) are non-medical factors that influence health outcomes, such as education, income, and social support, distinct from clinical or biological factors.
Option A (High body mass index): BMI is a clinical health outcome, not an SDOH.
Option B (Advanced age): Age is a demographic factor, not a primary SDOH, though it may interact with social factors.
Option C (Low literacy level): This is the correct answer. The NAHQ CPHQ study guide states, "Low literacy level is a social determinant of health, impacting health behaviors and access to care" (Domain 5). It affects understanding of medical instructions and health navigation.
Option D (Poorly managed chronic condition): This is a health outcome, not an SDOH.
CPHQ Objective Reference: Domain 5: Population Health and Care Transitions, Objective 5.4, "Incorporate SDOH into health strategies," includes literacy as an SDOH. The NAHQ study guide notes, "Literacy significantly influences health literacy and outcomes" (Domain 5).
Rationale: Low literacy is a key SDOH, impacting health management, as per CPHQ's population health principles.
Reference: NAHQ CPHQ Study Guide, Domain 5: Population Health and Care Transitions, Objective 5.4.
NEW QUESTION # 201
The data below shows 30-day readmission rates for heart failure patients by the primary language spoken and by gender with 95% confidence intervals in parentheses. Which group should be the priority target for reducing disparities in readmission rates?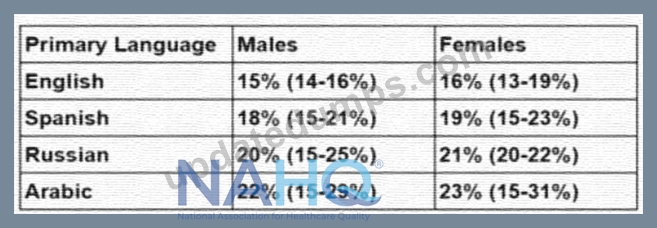
- A. Russian-speaking females
- B. All Russian speakers
- C. All Arabic speakers
- D. Arabic-speaking females
Answer: C
Explanation:
The goal is to identify the group with the greatest disparity in 30-day readmission rates for heart failure patients, focusing on primary language and gender, to prioritize interventions for reducing disparities. NAHQ CPHQ study materials emphasize that addressing disparities in population health involves targeting groups with the highest rates of adverse outcomes, such as readmissions, to achieve health equity. Disparities are often influenced by social determinants of health, including language barriers, which can affect communication, understanding of discharge instructions, and access to follow-up care.
The data shows readmission rates by language and gender, with 95% confidence intervals indicating the range of uncertainty around the point estimates. Let's analyze the rates:
* English: Males 15% (14-16%), Females 16% (13-19%)
* Spanish: Males 18% (15-21%), Females 19% (15-23%)
* Russian: Males 20% (15-25%), Females 21% (20-22%)
* Arabic: Males 22% (15-29%), Females 23% (15-31%)
First, compare the point estimates across groups. Arabic-speaking patients have the highest readmission rates:
22% for males and 23% for females, followed by Russian-speaking patients at 20% for males and 21% for females. English-speaking patients have the lowest rates at 15% for males and 16% for females. The confidence intervals show overlap between groups (e.g., Arabic males 15-29% overlaps with Russian males
15-25%), but the point estimates provide a clear ranking, with Arabic speakers consistently highest.
To assess disparities, calculate the overall rates for language groups by averaging male and female rates (since the options include "All Arabic speakers" and "All Russian speakers"):
* Arabic speakers: (22% + 23%) / 2 = 22.5%
* Russian speakers: (20% + 21%) / 2 = 20.5%
* Spanish speakers: (18% + 19%) / 2 = 18.5%
* English speakers: (15% + 16%) / 2 = 15.5%
Arabic speakers have the highest average readmission rate (22.5%), indicating the greatest disparity compared to English speakers (15.5%), a difference of 7 percentage points. Russian speakers have a 20.5% average rate, a 5-point difference from English speakers.
Now, compare the gender-specific options: Arabic-speaking females (A) have a rate of 23%, and Russian- speaking females (B) have a rate of 21%. While Arabic-speaking females have the highest single rate, the question asks for the priority group to reduce disparities, which often involves targeting the broadest group with the largest overall disparity. Option C, "All Arabic speakers," encompasses both males (22%) and females (23%), with an average of 22.5%, making it the group with the most significant disparity across both genders. Option D, "All Russian speakers," has a lower average rate (20.5%).
The confidence intervals, while wide for smaller groups like Arabic and Russian speakers, do not change the prioritization, as the point estimates consistently show Arabic speakers with the highest rates. NAHQ emphasizes targeting the group with the greatest disparity in outcomes to address health equity, particularly when language barriers (e.g., Arabic speakers) may contribute to higher readmissions due to communication challenges. Therefore, "All Arabic speakers" (C) should be the priority target for interventions, such as language-specific education or interpreter services, to reduce disparities in readmission rates.
Reference: NAHQ CPHQ Study Guide, Population Health and Care Transitions Section, "Addressing Health Disparities in Readmissions"; NAHQ CPHQ Practice Exam, Population Health Data Analysis for Equity.
NEW QUESTION # 202
......
Exam Questions and Answers for CPHQ Study Guide Questions and Answers!: https://www.updatedumps.com/NAHQ/CPHQ-updated-exam-dumps.html
Practice To CPHQ - UpdateDumps Remarkable Practice On your Certified Professional in Healthcare Quality Examination Exam: https://drive.google.com/open?id=1nVbHlN-mb24udzWvIuCCRZWJZCaSW8RN